No medicine, diet or exercise closes a leaking heart valve. Mild regurgitation usually needs no treatment at all, only regular echocardiograms; moderate to severe leaks that cause symptoms are treated by repairing or replacing the valve, either through open surgery or, for selected patients, through a thin tube passed from the groin (TEER for the mitral valve, TAVI for a narrowed aortic valve). Tablets such as diuretics and ACE inhibitors ease symptoms and protect the heart while you and your cardiologist decide.
What is a leaky heart valve, and why do medicines not fix it?
A leaky heart valve is a valve that does not close fully, so some blood flows backward with every beat. Doctors call this regurgitation. The NHS explains that the heart has 4 valves, that the mitral valve on the left side is one of the most often affected, and that a leaking valve makes the heart work harder to pump blood around the body. MedlinePlus describes the mitral version: blood leaks back into the left atrium each time the left ventricle contracts, less blood reaches the body, and over years the strained heart can fail.

The leak is a mechanical problem with the valve flaps (leaflets) or the structures that hold them. Cleveland Clinic splits mitral regurgitation into primary disease, where the valve itself is damaged (mitral valve prolapse is the most common cause in developed nations, rheumatic heart disease the most common worldwide), and secondary disease, where a stretched or scarred heart chamber pulls the leaflets apart (most often after a heart attack).
Because the fault is structural, no tablet makes the leaflets meet again. The NHLBI puts it plainly: doctors often start with lifestyle changes or medicines to manage symptoms, which may delay the need for a procedure, but repair or replacement may eventually be needed, and medicines continue afterwards. Any treatment that claims to "cure" regurgitation without a procedure is making a claim no listed authority supports.
When is watchful waiting the right answer?
Watchful waiting is the right answer for most people with a mild leak and no symptoms. MedlinePlus states that mitral regurgitation is mild most of the time, so no therapy or restriction is needed. For a leaking aortic valve it says the same: with no or mild symptoms you may not need treatment, but you will need regular exams and echocardiograms. The NHS adds that mild disease without symptoms may not need treatment and that regular check-ups are arranged to see whether it is worsening.
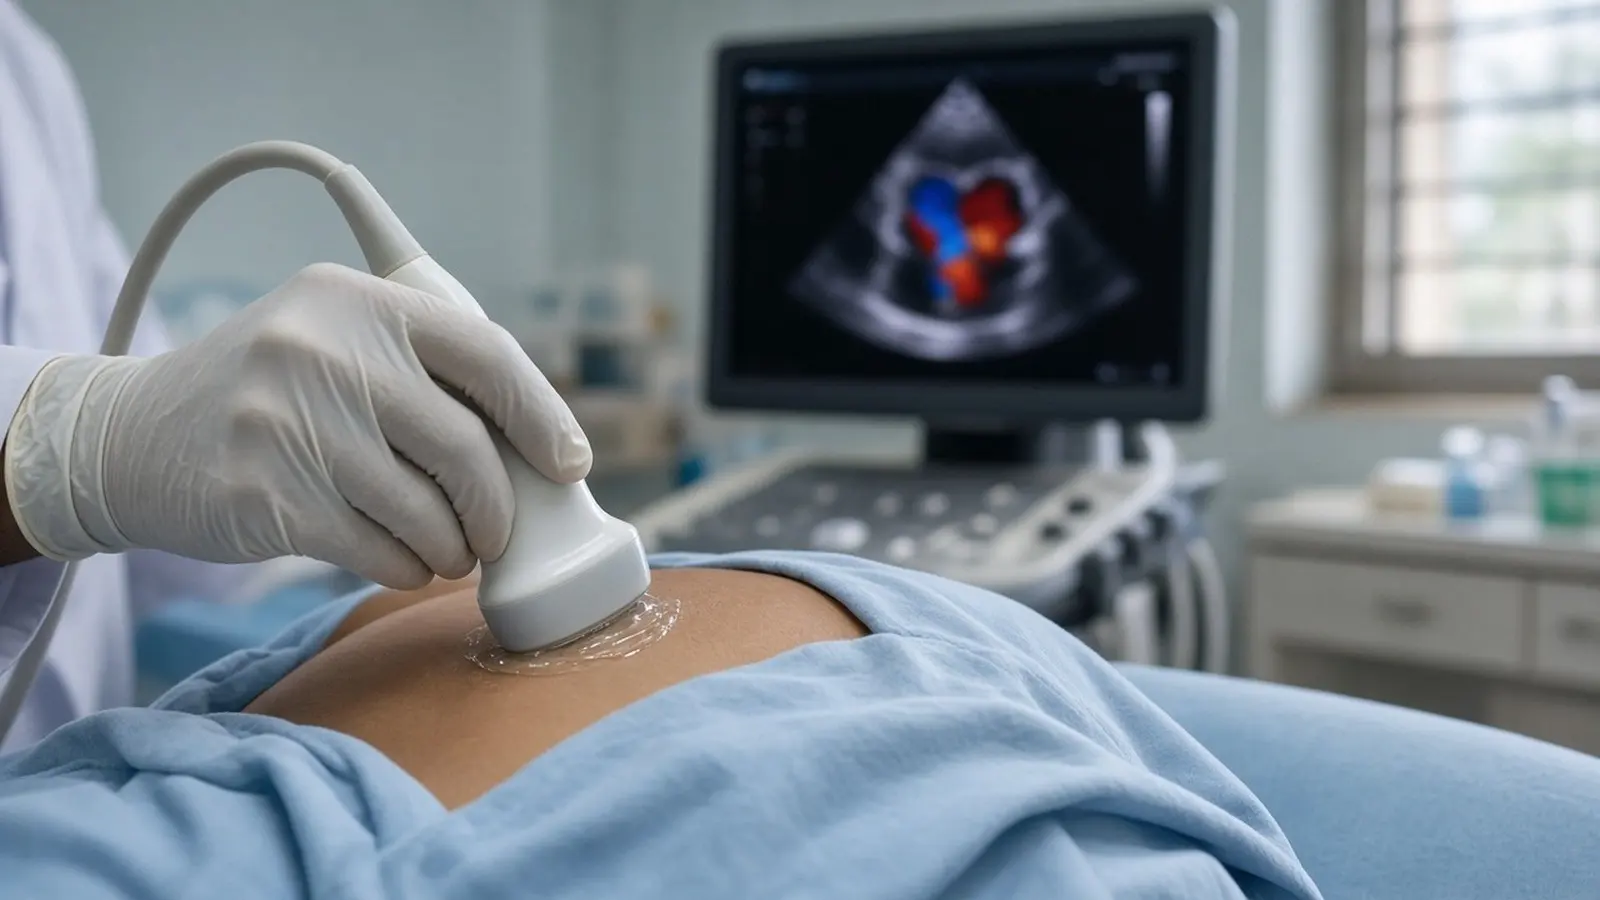
The echocardiogram is the test that grades the leak. Cleveland Clinic says a transthoracic echo is the commonly used test, a transoesophageal echo (probe passed down the gullet) gives a closer view, and cardiac CT, MRI, stress echo or catheterisation are added to judge severity or plan treatment. Cleveland Clinic grades the condition in stages A to D, D being the most severe, and says the more severe the stage, the more often follow-up visits and imaging are needed. The pages opened for this guide give no fixed interval, so ask your cardiologist how often you need the scan; see echo test cost for Indian prices.
MedlinePlus advises regular provider visits to track symptoms and heart function, and lists the changes that move a patient from waiting to treatment: heart function falling, the heart enlarging, or symptoms worsening. New breathlessness, palpitations or swollen ankles mean bring the next visit forward.
Which medicines are used for a leaky valve, and what do they do?
Medicines treat the consequences of the leak, not the leak. The NHS lists four groups for people with symptoms or severe disease; MedlinePlus and the NHLBI add detail on what each does.
| Medicine group (NHS list) | What it does | Who tends to get it |
|---|---|---|
| ACE inhibitors | Lower blood pressure and help protect the heart | High blood pressure or weakened heart muscle (MedlinePlus) |
| Diuretics (water tablets) | Reduce fluid build-up in the body and lungs | Breathlessness or swelling from fluid |
| Beta blockers | Slow the heart rate | Fast heart rate, rhythm problems |
| Anticoagulants (blood thinners) | Reduce the risk of blood clots | Atrial fibrillation, mechanical valve (Cleveland Clinic) |
MedlinePlus adds calcium channel blockers and rhythm-control drugs for some patients, a low-sodium diet, and limiting activity if symptoms develop. The NHLBI lists antibiotics to treat or prevent infections that inflame the heart, including rheumatic fever, which matters in India.
Two points keep expectations honest. First, MedlinePlus says symptoms can usually be controlled with medicine, which is a real benefit. Second, the NHLBI is clear that repair is recommended for new or worsening symptoms even on medicines. Do not stop or change any of these drugs without the prescribing doctor; anticoagulants in particular need regular blood tests when warfarin is used.
What catheter procedures treat a leaky valve without open surgery?
Two catheter procedures avoid opening the chest, and they treat different valves. Transcatheter edge-to-edge repair (TEER, best known by the MitraClip device) treats a leaking mitral or tricuspid valve. Cleveland Clinic describes it as a minimally invasive procedure under general anaesthesia that takes about two hours or less: a catheter enters the femoral vein in the groin, crosses to the left side of the heart, and places one or more small clips on the leaflet edges so they close more fully. An echo checks the result. Patients spend one or two days in hospital and may return to work and driving in about a week.

Cleveland Clinic says TEER is offered when the case is severe or when surgery would be too risky because of other medical problems, and that it is not right for everyone. The NHLBI describes the same device route as an option for people with mitral regurgitation who should not have open-heart surgery. Listed risks include bleeding, infection, clots, clip detachment, rhythm problems and valve narrowing.
Transcatheter aortic valve implantation (TAVI, also called TAVR) replaces the aortic valve through the femoral artery. Both the NHLBI and Cleveland Clinic describe it as a treatment for aortic stenosis, a narrowed valve; neither page lists aortic regurgitation. MedlinePlus says a catheter-implanted valve for aortic regurgitation is receiving increasing interest and may become more common, meaning it is not yet the standard route. Cleveland Clinic also lists transcatheter mitral valve replacement as a less invasive option in selected cases.
What do the trials say about TEER and MitraClip?
The two randomised trials of MitraClip in heart-failure patients with secondary mitral regurgitation reached opposite conclusions, and both results matter when a cardiologist decides who should have the procedure.
| Trial | Patients | Main result |
|---|---|---|
| COAPT (US/Canada) | 614; NYHA class II to IV, LVEF 20% to 50%, maximal medicines confirmed by a committee | Heart-failure admissions 35.8% vs 67.9% per patient-year at 2 years; death 29.1% vs 46.1% |
| COAPT at 5 years | 302 clip vs 312 medicines | Heart-failure admission 61% vs 83% (HR 0.49); death 57.3% vs 67.2% (HR 0.72) |
| MITRA-FR (France) | 304; LVEF 15% to 40% | Death or heart-failure admission at 1 year 54.6% vs 51.3% (p = 0.53), no difference |
Pibarot and colleagues, writing in European Heart Journal Cardiovascular Imaging, explain the gap: COAPT required a larger leak (effective orifice above 30 mm², against 20 mm² in MITRA-FR) in less dilated hearts, so the leak itself drove the heart failure; in MITRA-FR the weak ventricle drove it and clipping the valve could not help. COAPT also insisted on optimised medicines first. A 2024 commentary on the five-year data still raises doubts, noting that most echo measurements in the clip group did not change and that modern heart-failure drugs were under-used in the control arm.
Device freedom from complications in COAPT was 96.6% at 12 months, so the procedure is safe in experienced hands, but benefit depends on selecting the right patient, not on the device alone.
When is open surgery still the better choice?
Open surgery is still the standard treatment for a severe leak in a patient fit enough to have it, because it can repair the valve rather than clip it. The NHS says surgery is used for severe disease: the valve is repaired if it is not seriously damaged, or replaced with an artificial valve or one made from human or animal tissue if repair is not possible. MedlinePlus states that surgery can cure aortic insufficiency and relieve symptoms, unless heart failure or other complications have already developed, and that people with angina or heart failure from aortic regurgitation do poorly without treatment.
The NHLBI lists what surgical repair involves: sewing, reshaping or patching the leaflets, shortening or replacing the cords that support the valve, and annuloplasty, which tightens the valve base with a ring. Repair can improve symptoms, but problems sometimes return.
If replacement is needed, the NHLBI sets out the trade-off:
- Biological (tissue) valves: no lifelong blood thinners, but they wear out and may need replacing.
- Mechanical valves: last longer, but need lifelong blood thinners and carry extra risks in pregnancy.
Risks of any valve operation, per the NHLBI, include stroke, clots, bleeding, kidney or heart injury, and a new valve that leaks because it does not fit well. Timing matters: MedlinePlus says surgery is considered when heart function is poor, the heart is enlarged, or symptoms worsen, which is why echo surveillance during watchful waiting is not optional.
What can you do yourself, and when must you not wait?
You can protect the heart around the valve, reduce the load on it, and avoid a second attack of the disease that caused the leak. The NHLBI recommends heart-healthy food, a healthy weight, managing stress, regular physical activity agreed with your doctor, and quitting smoking. Cleveland Clinic adds controlling blood pressure, yearly check-ups, and seeing a provider for frequent sore throats with fever or a past history of rheumatic fever, because repeat streptococcal infections damage valves further.
That last point is an Indian problem. A clinico-observational study in rural Andhra Pradesh published in the Journal of Cardiovascular Disease Research found rheumatic heart disease in 9.7 per 1,000 people, mitral regurgitation was the single most common lesion (43.4% of cases), and the authors note that India contributes 25% to 50% of the global burden. A sore throat treated properly, and penicillin prophylaxis when prescribed, is valve care.
See a doctor the same day if breathlessness worsens, you cannot lie flat, your ankles swell, or your heart races. Call 112 or go to the nearest emergency department for severe breathlessness, chest pain that spreads or lasts more than 15 minutes, or a home pulse oximeter reading that is low; Cleveland Clinic lists these as signs of acute heart failure.
Find a cardiologist who performs echocardiography and ask whether your hospital has a heart team that offers both surgery and TEER; our hospital directory lists cardiac centres by city. This guide is general information from the sources listed below, not medical advice; a registered doctor makes decisions with you.
